

Genetic testing for lactose intolerance identifies specific DNA variants in the MCM6 gene region that regulate lactase enzyme production, enabling clinicians to distinguish primary lactase non-persistence from other causes of dairy intolerance without the time and patient burden of breath hydrogen or lactose tolerance tests. The test detects single nucleotide polymorphisms associated with continued lactase expression into adulthood, a trait that evolved independently in multiple populations practicing dairy pastoralism. Unlike functional tests that measure current lactase activity, lactose intolerance genetic testing reveals an individual’s inherited predisposition, offering particular clinical value when symptoms are ambiguous, elimination diets prove inconclusive, or functional testing carries contraindications.
The diagnostic approach has gained traction in clinical gastroenterology and personalized nutrition protocols as sequencing costs have declined and understanding of the genetic architecture has matured. Testing typically examines the C/T-13910 and G/A-22018 variants upstream of the LCT gene, though additional variants relevant to non-European ancestry groups are increasingly incorporated into comprehensive panels. Results stratify patients into lactase-persistent (homozygous or heterozygous for persistence alleles) or lactase non-persistent (homozygous for ancestral alleles) genotypes, informing dietary counseling, symptom management strategies, and decisions about empiric calcium supplementation in populations at risk for inadequate intake.
For researchers and healthcare professionals, genetic testing complements rather than replaces clinical assessment. It addresses a defined question about hereditary lactase regulation but cannot quantify symptom severity, identify concurrent conditions such as small intestinal bacterial overgrowth, or account for the lactose threshold variation observed among non-persistent individuals. Integration into diagnostic algorithms requires understanding test limitations, ethnic-specific allele frequencies, and the distinction between genotype and phenotype. This article outlines the clinical contexts where genetic testing adds diagnostic clarity, the pathways through which patients and providers access testing, result interpretation frameworks, and the collaborative care models that translate genetic information into improved patient outcomes.
What Lactose Intolerance Genetic Testing Measures
Lactose intolerance genetic testing identifies specific DNA variants in regulatory regions near the LCT gene on chromosome 2, which encodes lactase, the enzyme responsible for breaking down lactose. The test primarily targets two well-characterized single nucleotide polymorphisms (SNPs): the -13910 C/T variant located in the MCM6 gene and the -22018 G/A variant in the same regulatory region. These polymorphisms influence whether lactase production persists into adulthood or declines after weaning, the natural pattern for most mammals. The presence of the T allele at position -13910 or the A allele at position -22018 correlates with continued lactase expression throughout life, termed lactase persistence. Individuals homozygous for the C allele at -13910 or the G allele at -22018 typically experience lactase non-persistence, reducing their ability to digest lactose efficiently.
The test functions as a genotype-based risk assessment rather than a direct measure of lactase enzyme activity in the small intestinal brush border. A genetic result indicating lactase non-persistence means the individual carries alleles associated with declining lactase production after childhood, increasing the likelihood of lactose malabsorption if dietary lactose intake exceeds residual enzyme capacity. However, genotype does not predict symptom severity, which depends on multiple factors including residual enzyme levels, gut microbiome composition, colonic transit time, and individual symptom thresholds. Some genetically predisposed individuals remain asymptomatic or tolerate moderate lactose amounts without distress.
Crucially, genetic testing distinguishes primary lactose intolerance, an inherited trait reflecting normal developmental lactase decline, from secondary lactose intolerance resulting from intestinal damage. Conditions such as celiac disease, Crohn’s disease, acute gastroenteritis, or chemotherapy-induced enteropathy can temporarily or permanently damage lactase-producing enterocytes, causing lactose malabsorption regardless of genetic background. A genetic test showing lactase persistence genotype in a symptomatic patient directs clinical attention toward secondary causes or alternative diagnoses. Conversely, a non-persistence genotype confirms genetic predisposition but does not exclude concurrent gastrointestinal pathology. This distinction makes genetic testing a valuable diagnostic adjunct when integrated with symptom history, dietary patterns, and complementary assessments such as hydrogen breath testing or lactose tolerance challenges.
Who Should Consider Genetic Testing for Lactose Intolerance
Genetic testing for lactose intolerance serves as a diagnostic tool in specific clinical contexts where genotype information clarifies underlying physiology and guides management. Healthcare providers typically recommend testing when symptoms warrant investigation and alternative assessment methods are impractical or inconclusive.
Patients experiencing chronic gastrointestinal symptoms, bloating, abdominal pain, diarrhea, or flatulence, of unclear origin represent prime candidates for genetic evaluation. When these symptoms persist despite initial workup and differential diagnosis remains broad, genotyping the MCM6 regulatory region can distinguish primary lactase non-persistence from other conditions presenting with similar manifestations. This approach proves particularly valuable when patients have not identified dietary triggers through symptom diaries or when multiple food intolerances complicate clinical assessment.
Individuals seeking diagnostic confirmation without undergoing hydrogen breath testing or dietary elimination trials benefit from genetic analysis. Breath testing requires fasting, controlled lactose administration, and serial sample collection over several hours, making it inconvenient for many patients. Elimination diets demand weeks of strict adherence and subsequent reintroduction protocols. Genetic testing bypasses these requirements, delivering definitive information about genetic susceptibility to lactase decline through a single sample.
Testing holds particular clinical utility in the following scenarios:
- Patients unable to complete hydrogen breath testing due to recent antibiotic use, gastrointestinal motility disorders, or respiratory conditions affecting sample quality
- Individuals from populations with high lactase non-persistence prevalence (East Asian, West African, Arab, Jewish, Greek, or Southern Italian ancestry) seeking to understand symptom etiology
- Cases where lactose tolerance testing is contraindicated, including patients with diabetes mellitus where lactose loading could destabilize glycemic control
- Clinical investigations where distinguishing congenital lactase deficiency from acquired secondary intolerance informs therapeutic strategy
Pediatric testing requires careful consideration of developmental physiology. Lactase production naturally remains high during infancy to support milk digestion, then declines after weaning in genetically predisposed children. This transition typically occurs between ages two and twelve, with timing varying by genotype and population background. Clinicians should interpret genetic results in children within this developmental context, recognizing that heterozygous genotypes may manifest as intermediate phenotypes with partial enzyme activity. Testing before age five may not correlate well with current symptoms, as lactase decline has not yet fully manifested even in homozygous non-persistence genotypes.
Genetic evaluation also assists in family planning contexts when both parents carry lactase non-persistence alleles and wish to understand inheritance patterns for offspring, though this represents a secondary rather than primary indication for testing.
How to Access and Complete Lactose Intolerance Genetic Testing

Accessing lactose intolerance genetic testing follows two primary routes: physician-ordered testing through clinical laboratories and direct-to-consumer services. Each pathway involves distinct procedural steps, sample collection protocols, and result delivery mechanisms integrated into the broader genomic diagnostic workflow.
Physician-Ordered Clinical Testing
Patients pursuing clinical testing begin with a consultation where a gastroenterologist, primary care physician, or genetics specialist evaluates symptoms, medical history, and family patterns. The ordering provider determines whether genetic testing is appropriate given the clinical context and discusses how results will inform treatment planning.
Once testing is authorized, the provider submits a requisition to a hospital-affiliated molecular diagnostics laboratory or a reference genetics laboratory. This requisition specifies the genetic variants to be analyzed, typically the -13910 C/T polymorphism in European-ancestry populations or expanded panels including -22018 G/A for diverse ancestry groups.
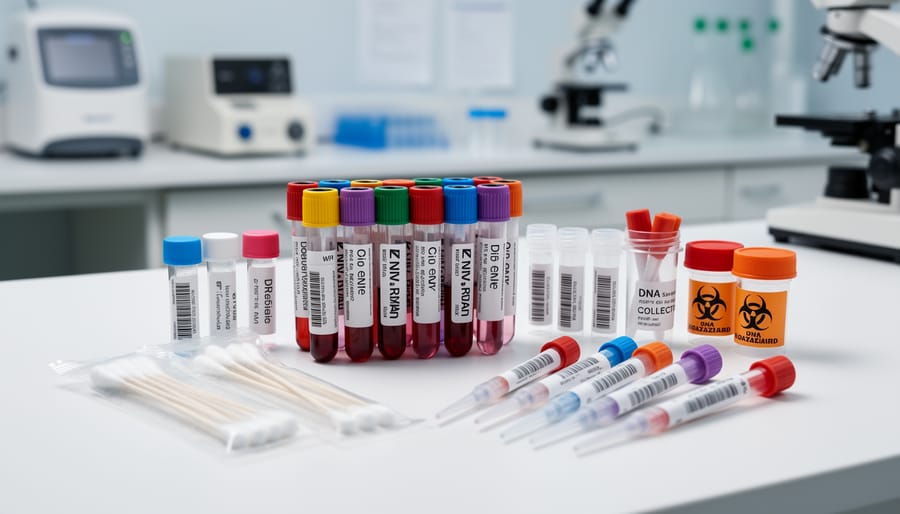
Sample collection occurs either in a clinical setting or at a contracted phlebotomy center. The most common collection methods are buccal swabs, which patients self-administer by rubbing a sterile swab against the inner cheek for several seconds, or venous blood draws performed by trained phlebotomists. Buccal samples are preferred in pediatric cases due to minimal invasiveness. The collected sample is labeled with patient identifiers, sealed in biohazard-compliant packaging, and transported to the processing laboratory under chain-of-custody protocols.
Laboratories extract genomic DNA and perform polymerase chain reaction amplification followed by sequencing or genotyping assays targeting the relevant regulatory regions. Quality control steps verify sample integrity and genotype calling accuracy. Results are compiled into a clinical report that includes the patient’s genotype, interpretation of lactase persistence or non-persistence risk, and relevant population frequency data.
Providers receive results through secure electronic health record systems or laboratory portals and schedule follow-up appointments to discuss findings with patients.
Direct-to-Consumer Testing Pathways
Direct-to-consumer services allow individuals to order genetic testing without physician involvement, though availability and regulatory oversight vary by jurisdiction. Customers select a testing kit online, complete payment, and receive a collection kit by mail.
The kit contains sterile saliva collection tubes or buccal swabs, biohazard bags for return shipping, and detailed instructions. Patients provide samples at home, typically by depositing saliva into a stabilization tube or swabbing the inner cheek multiple times. Samples must be registered online using a unique barcode to link the specimen to the customer’s account while maintaining laboratory blinding protocols.
After collection, patients seal the sample container, place it in the provided return mailer with prepaid postage, and ship it to the company’s contracted laboratory. Some services require samples to be shipped on specific days to minimize transit time and maintain DNA stability.
Laboratory processing follows similar molecular protocols as clinical testing. Results are delivered through secure online portals, often accompanied by educational materials explaining genotype implications for lactose digestion. Some services offer optional genetic counseling consultations to help customers interpret findings and discuss dietary adjustments.
Pre-Test Considerations
Before proceeding with either pathway, individuals should understand test scope and limitations. Genetic testing identifies predisposition to primary lactose intolerance but does not diagnose current lactase enzyme levels or distinguish secondary causes related to gastrointestinal disease. Informed consent documentation explains these limitations, data privacy protections, and potential psychological impacts of learning genetic risk information.
Patients with complex medical histories, atypical symptoms, or concerns about result interpretation benefit from pre-test genetic counseling to clarify whether testing aligns with their diagnostic needs and to prepare for decision-making based on results.
Understanding Your Rights and Test Result Interpretation
When you undergo genetic testing for lactose intolerance, you acquire specific rights concerning how your genetic information is handled, stored, and disclosed. In the United States, the Genetic Information Nondiscrimination Act (GINA) prohibits health insurers and employers from using genetic test results to make decisions about coverage eligibility or employment. However, GINA does not extend to life insurance, disability insurance, or long-term care insurance, where genetic information may influence underwriting decisions. Under the European Union’s General Data Protection Regulation (GDPR), genetic data receives classification as a special category of personal data requiring explicit consent for processing, with enhanced rights to access, correct, or request deletion of your genetic information from laboratory databases.
Most laboratories and testing services allow you to specify result disclosure preferences during the consent process. You can typically designate whether results should be released only to your ordering physician, made available through a patient portal, or shared with additional healthcare providers involved in your care. Data storage policies vary: some laboratories retain raw genetic data indefinitely for quality assurance and potential reanalysis as scientific understanding evolves, while direct-to-consumer companies may offer options to download and delete your information after a specified retention period. Review storage and sharing policies before testing, particularly if you have concerns about future insurance applications or employment in jurisdictions where genetic protections are limited.
| Genotype at -13910 Position | Predicted Phenotype | Clinical Interpretation |
|---|---|---|
| C/C | Lactase non-persistence | High probability of declining lactase activity after childhood; symptoms likely with lactose consumption |
| C/T | Intermediate persistence | Partial lactase activity retention; tolerance varies individually and may change with age |
| T/T | Lactase persistence | Continued lactase production into adulthood; symptoms unlikely from lactose alone |
Interpreting your genetic test results requires understanding what specific genotypes predict. Homozygous C/C results at the -13910 position in the MCM6 gene indicate you carry two copies of the lactase non-persistence allele, suggesting you will experience declining lactase enzyme production as you age. Homozygous T/T results indicate lactase persistence, with continued enzyme production throughout adulthood. Heterozygous C/T results present an intermediate scenario: you may retain partial lactase activity, with tolerance depending on factors including lactose dose, gut microbiome composition, and individual symptom thresholds. These results are probabilistic rather than deterministic, they indicate genetic predisposition, not guaranteed clinical outcomes.
Genetic findings should always undergo clinical interpretation alongside symptom assessment and functional testing. A patient with lactase non-persistence genotype who reports no digestive symptoms after dairy consumption may have adapted gut microbiota that ferment lactose efficiently or may habitually consume only small lactose amounts. Conversely, someone with a lactase persistence genotype experiencing gastrointestinal distress after dairy requires evaluation for alternative diagnoses such as milk protein allergy, irritable bowel syndrome, or small intestinal bacterial overgrowth. Genetic results inform dietary counseling and diagnostic reasoning but do not replace hydrogen breath testing or elimination-rechallenge protocols when symptoms remain unexplained.
You have an obligation to engage in shared decision-making with your healthcare team regarding how genetic results influence your care plan. Discuss with your gastroenterologist or primary care physician whether dietary modification, enzyme supplementation, or additional diagnostic workup is appropriate based on your complete clinical picture. Genetic counselors serve a vital role in this process, particularly when results conflict with symptom patterns or when you have questions about implications for family members. They can explain inheritance patterns, discuss limitations of current testing panels, and help you weigh the benefits and risks of cascade testing in relatives who may share your genetic profile.
Where to Access Clinical Support and Genetic Counseling
Genetic test results for lactose intolerance are most valuable when interpreted within a clinical context, requiring collaboration among multiple specialists. Gastroenterologists who specialize in functional gastrointestinal disorders can integrate genetic findings into comprehensive diagnostic evaluations, distinguishing primary lactase deficiency from secondary causes related to inflammatory bowel disease, celiac disease, or small intestinal bacterial overgrowth. These specialists assess symptom patterns, order complementary functional tests when indicated, and coordinate multidisciplinary care plans.
Registered dietitians with expertise in gastrointestinal nutrition play a central role in translating genetic results into practical dietary strategies. They evaluate individual tolerance thresholds, recommend appropriate dairy alternatives or enzyme supplementation, and design nutritionally adequate eating patterns that maintain calcium and vitamin D intake while managing symptoms. Dietitians can also address co-existing food intolerances that may complicate symptom interpretation.
Institutional resources include academic medical centers with genomic medicine programs that offer coordinated gastroenterology, nutrition, and genetic counseling services under one umbrella. Professional directories maintained by the American College of Medical Genetics and Genomics and the National Society of Genetic Counselors allow patients to locate certified specialists by geographic region and subspecialty expertise. Many practices now offer telehealth consultations, expanding access to genetic counseling in areas where local specialists are unavailable.
Seek additional support when symptoms persist despite dietary modification based on genetic results, when family history suggests unusual inheritance patterns, or when genetic findings conflict with clinical presentation. Atypical presentations, such as symptom onset in infancy or sudden adult-onset intolerance in populations with high lactase persistence prevalence, warrant thorough evaluation. Consultation with specialists who understand how genetics guide care across diverse conditions ensures results are interpreted accurately within the broader clinical picture, avoiding both overreliance on genetic data and dismissal of relevant genetic contributions to symptom etiology.

How to Apply or Complete the Process
The process for completing lactose intolerance genetic testing varies depending on whether you pursue clinical or direct-to-consumer pathways, but both follow structured steps.
For physician-ordered testing, your healthcare provider determines whether the test is clinically appropriate based on your symptoms and medical history. If recommended, the provider completes a requisition form specifying the genetic variants to be analyzed, typically MCM6 polymorphisms associated with lactase persistence. Sample collection occurs either at the ordering clinic or a designated laboratory collection site. Most tests use buccal swabs, though some require blood draws. The specimen is sent to a reference laboratory for DNA extraction and genotyping.
Direct-to-consumer testing follows a different sequence. After selecting a testing company that offers lactose intolerance genetic analysis, you order a kit online. The kit arrives with collection materials (usually a saliva tube or cheek swab), instructions, and a prepaid return envelope. You register the kit using a unique identifier, collect your sample following the protocol provided, and return it via mail. The laboratory processes the sample and uploads results to a secure online portal.
Both pathways require you to review consent forms acknowledging how your genetic data will be used, stored, and protected. Clinical testing may involve pre-test counseling to discuss implications and limitations. Regardless of pathway, results should be interpreted with professional guidance to inform clinical decisions and dietary management strategies.
Where to Get Official Help
For clinical interpretation and pre-test consultation, contact board-certified genetic counselors through the National Society of Genetic Counselors directory at, which maintains a searchable database of professionals specializing in metabolic genetics and gastrointestinal disorders. Many counselors now offer telehealth appointments for patients in multiple states.
Gastroenterology specialists affiliated with academic medical centers typically provide the most integrated approach to genetic testing within broader diagnostic workups. The American College of Gastroenterology () offers a physician finder tool to locate specialists experienced in functional gastrointestinal disorders and genetic diagnostics.
For nutrition counseling following genetic test results, seek registered dietitians credentialed through the Academy of Nutrition and Dietetics (). Request dietitians with expertise in lactose restriction, dairy alternatives, and calcium adequacy to ensure dietary modifications support both symptom management and nutritional needs.
Laboratory-specific questions about specimen requirements, processing timelines, or result delivery should be directed to the testing laboratory’s client services department. Most reference laboratories maintain dedicated genetic testing support lines staffed by laboratory genetic counselors who can address technical questions about test methodology and result interpretation frameworks without providing individualized medical advice.
Frequently Asked Questions
Frequently Asked Questions
Genetic testing for lactose intolerance raises questions from both patients seeking diagnosis and clinicians integrating genomic tools into practice. The following addresses recurring queries about test utility, interpretation, and clinical application.
Can genetic testing replace hydrogen breath testing?
No, these methods assess different aspects and function as complementary tools. Genetic testing identifies inherited predisposition to lactase non-persistence through DNA variants, while breath testing measures current functional lactose digestion capacity, which may be compromised by secondary causes such as gastrointestinal disease or medication effects.
Does a positive genetic result mean I must avoid all dairy?
No, tolerance varies widely even among individuals with identical genotypes. Dietary management should be individualized based on symptom severity, residual enzyme activity, and personal tolerance thresholds, with many patients tolerating small dairy portions or fermented products despite genetic susceptibility.
Can children be tested for lactose intolerance genes?
Yes, genetic testing is technically feasible at any age, but interpretation must account for normal developmental lactase decline. Most genetically predisposed children retain sufficient enzyme activity during early childhood, with symptoms typically emerging after age five as programmed downregulation occurs.
How do ancestry and population genetics affect test interpretation?
Lactase persistence allele frequencies vary dramatically across populations, affecting pre-test probability and result interpretation. Northern European ancestry correlates with higher persistence rates, while East Asian, West African, and some Mediterranean populations show predominant non-persistence patterns, influencing clinical expectations and population differences in test yield.
Clinicians frequently ask whether genetic results directly inform therapeutic decisions regarding enzyme supplementation or dairy exclusion protocols. While test outcomes provide valuable context for dietary counseling, they do not prescribe specific interventions. A patient with confirmed genetic non-persistence may still tolerate moderate lactose intake through adaptive gut microbiome shifts, calcium-fortified alternatives, or enzyme supplements taken strategically with meals. Conversely, individuals with persistence genotypes occasionally report symptoms due to secondary lactose maldigestion from concurrent conditions affecting intestinal mucosa.
The actionability of genetic testing lies primarily in refining diagnostic workup rather than dictating treatment algorithms. Results help distinguish primary from secondary causes when symptoms persist despite dietary modification, guide clinicians in deciding whether to pursue invasive endoscopic evaluation for alternative diagnoses, and support patient understanding of symptom origins. For families with multiple affected members, genetic confirmation can clarify inheritance patterns and inform screening decisions for relatives, though routine cascade testing remains uncommon given lactose intolerance’s benign, manageable nature compared to high-risk hereditary conditions.
Genetic testing for lactose intolerance represents a valuable tool within a broader diagnostic framework, but it functions most effectively when integrated with clinical assessment, symptom evaluation, and functional testing rather than as a standalone determinant. The identification of LCT and MCM6 gene variants provides insight into an individual’s genetic predisposition to lactase non-persistence, yet this information gains clinical relevance only through collaboration among gastroenterologists, dietitians, and genetic counselors who can contextualize results within each patient’s unique presentation and health history.
The collaborative diagnostic model ensures that genetic findings inform rather than dictate management strategies. Gastroenterologists contribute expertise in ruling out secondary causes of lactose intolerance and other gastrointestinal conditions that may mimic or coexist with primary lactase deficiency. Dietitians translate genetic risk profiles into personalized nutrition guidance, recognizing that tolerance thresholds vary widely even among individuals with identical genotypes. Genetic counselors facilitate informed decision-making by explaining inheritance patterns, addressing family planning considerations, and clarifying the probabilistic nature of genetic risk assessment.
Current research continues to expand our understanding of lactose digestion genetics beyond the well-characterized -13910 and -22018 variants. Investigators are exploring additional regulatory polymorphisms, modifier genes that influence lactase expression levels, and epigenetic factors that may explain phenotypic variation not fully captured by existing tests. These advances may eventually enable more refined testing panels that account for population-specific variants and improve predictive accuracy across diverse ancestries.
Healthcare professionals and patients should remain engaged with emerging developments in genomic medicine as they apply to digestive health. Consulting qualified specialists ensures that testing decisions align with clinical needs, that results receive appropriate interpretation, and that management plans reflect the latest evidence-based approaches to lactose intolerance diagnosis and dietary optimization.


